Women have been taught to accept menopause symptoms as an inevitable part of aging—but outdated medicine and a failure to treat women as whole people are often to blame.
Gilda was a patient of mine in her mid-50s who had bounced around from her orthopedist to her gynecologist for hip pain and recurring urinary tract infections (UTIs). The X-ray showed wear and tear in her hip joint. “Take anti-inflammatories and see you in 10 years for a hip replacement,” the orthopedist said. The gynecologist treated her UTIs with antibiotic after antibiotic until Gilda’s digestive tract cried for mercy.
By the time Gilda reached my office, she was worn out. The message seemed clear: This was the natural course of aging, and she should get used to the patient role.
“It’s depressing,” she told me.
… The system has taught her that her symptoms are just the natural consequences of being a middle-aged or older woman.

The hip pain had kept her from her regular walks with neighbors. She’d stopped gardening because crouching and weeding was uncomfortable, too. She’d also stopped having sex with her husband which only made her feel more blue.
The irony is that it didn’t take anything fancy—not an X-ray or lab test but rather a simple conversation—to figure out what was actually going on. When I asked Gilda about vaginal dryness, sexual discomfort and whether anyone had offered her hormone therapy, she looked at me like I was from the moon. But it was clear she had classic postmenopausal estrogen deficiency, which was causing the UTIs and the pelvic floor dysfunction that was causing the hip pain. After a few months of vaginal estrogen and pelvic floor physical therapy, her pain receded. Her X-ray didn’t change. But the muscles that undergirded her hip joint had improved.
It’s not that her doctors were bad. Not at all. They were treating the X-ray. They were treating the urine results.
What they weren’t doing was treating Gilda as a whole person.
… She had classic postmenopausal estrogen deficiency, which was causing the UTIs and the pelvic floor dysfunction that was causing the hip pain. After a few months of vaginal estrogen and pelvic floor physical therapy, her pain receded.
Like so many physicians who were never trained on menopause or hormone therapy, Gilda’s gynecologist was practicing based on outdated information—that estrogen causes cancer or that there’s some reason not to be on hormone therapy.
This is, of course, why women have been dismissed for generations, and why there’s been a decades-long lag between medical evidence and clinical practice, layered on top of a research establishment that barely studied female bodies to begin with.
And I’ll say this as a physician: I was trained with the same mantra. That hormone therapy was only for women who were absolutely miserable, and that if we were to prescribe it, it was for the least amount of time at the smallest dose.
That was completely wrong.
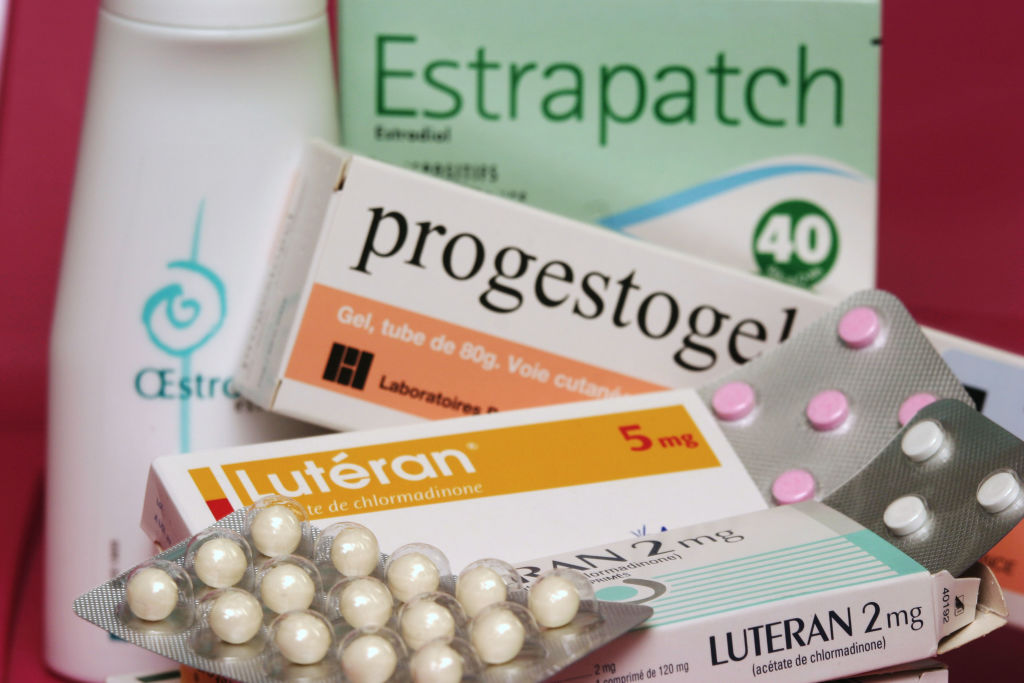
The mangling of that messaging is … responsible for terrifying generations of women away from taking the very things—estrogen and progesterone—that improve the immediate symptoms of menopause …
In 2002, part of the Women’s Health Initiative study was halted prematurely for a press release that essentially stated that hormone therapy caused breast cancer—when in actuality, the women who took estrogen alone (those without a uterus) actually had a reduced risk for breast cancer.
The mangling of that messaging is in large part responsible for scaring a generation of physicians off prescribing hormone therapy and terrifying generations of women away from taking the very things—estrogen and progesterone—that improve the immediate symptoms of menopause (such as hot flashes, night sweats, vaginal dryness and recurrent UTIs) and prevent the long-term consequences of estrogen depletion like osteoporosis, heart disease and premature cognitive decline.

The woman being dismissed, like my patient Gilda, is almost always someone who is educated and motivated to be well. She just hasn’t been given access to someone who will listen to her true story and who has updated information about the relative safety profile of hormone therapy, particularly vaginal estrogen, which is safe for the vast majority of menopausal women, including many with a breast cancer history.
Adding insult to injury, this is also the same woman who is running everyone else’s healthcare. Booking her kids’ appointments. Managing her parents’ medications. Tracking her husband’s cholesterol. She is fluent in advocacy for everyone but herself—partly because the system has taught her that her symptoms are just the natural consequences of being a middle-aged or older woman.

The solution here is, of course, to advocate for your needs. To find a doctor who has access to updated information and who is menopause certified. To advocate for a primary care doctor who knows your name, not just your diagnosis codes.
It’s also to recognize that every time you refuse to accept a doctor telling you, “That’s just aging,” you aren’t just advocating for yourself. You’re doing structural work. You’re demanding to be seen as a full person, not as a set of body parts.
The questions women ask in exam rooms are how the gap between medical evidence and clinical practice closes. It’s how we close the disparity between men’s health and women’s health.
Health, after all, isn’t about having all the answers. It’s about asking better questions—of yourself, and of the people responsible for your care.
*
A note from Ms. editors: We want to hear from you for The Majority, a new campaign collecting stories about how reproductive freedom has enabled readers to build the lives they want and need. Poll after poll shows a majority of Americans support reproductive healthcare access. Yet public debate overlooks the lives shaped by abortion access, contraception, IVF, miscarriage care, maternal healthcare or comprehensive sex education—countless women who chose to pursue an education, have children, not have children, protect their health and chart their own future. Add your voice and complete the sentence: “Access to reproductive choices gave me the freedom to….” Together, these stories will help show not only why reproductive freedom remains a majority value, but also what it makes possible.